
Automation & AI
Where AI earns its keep in a healthcare practice
The promise of AI in a practice is rarely the problem — the deployment is. Practices that chase the headline capability end up with a tool nobody trusts. Practices that start from the admin work nobody wants to do end up with automation that sticks, frees hours, and earns the credibility to take on more. The difference is choosing the right first workload.
Health MediCo™ Technology · 18 June 2026 · 7 min read
Start with the work nobody wants
The automation that sticks is the automation that removes a task the team already resents: appointment reminders and no-show follow-up, roster gap alerts, document classification, and the first-draft structuring of consultation notes. These are high-volume, low-judgement, and easy to verify — exactly the profile where AI delivers reliably today.
High-judgement work — diagnosis, treatment decisions, anything that lands on a patient's record unsigned — is not where to start. It's where AI will matter eventually, but only after the team trusts the platform on the lower-stakes work first.
- Begin with reminders, classification and first-draft notes — not diagnosis
- Every AI output needs a human checkpoint before it touches a patient record
- Measure the hours returned, not the features added
Staffing and rosters as an automation problem
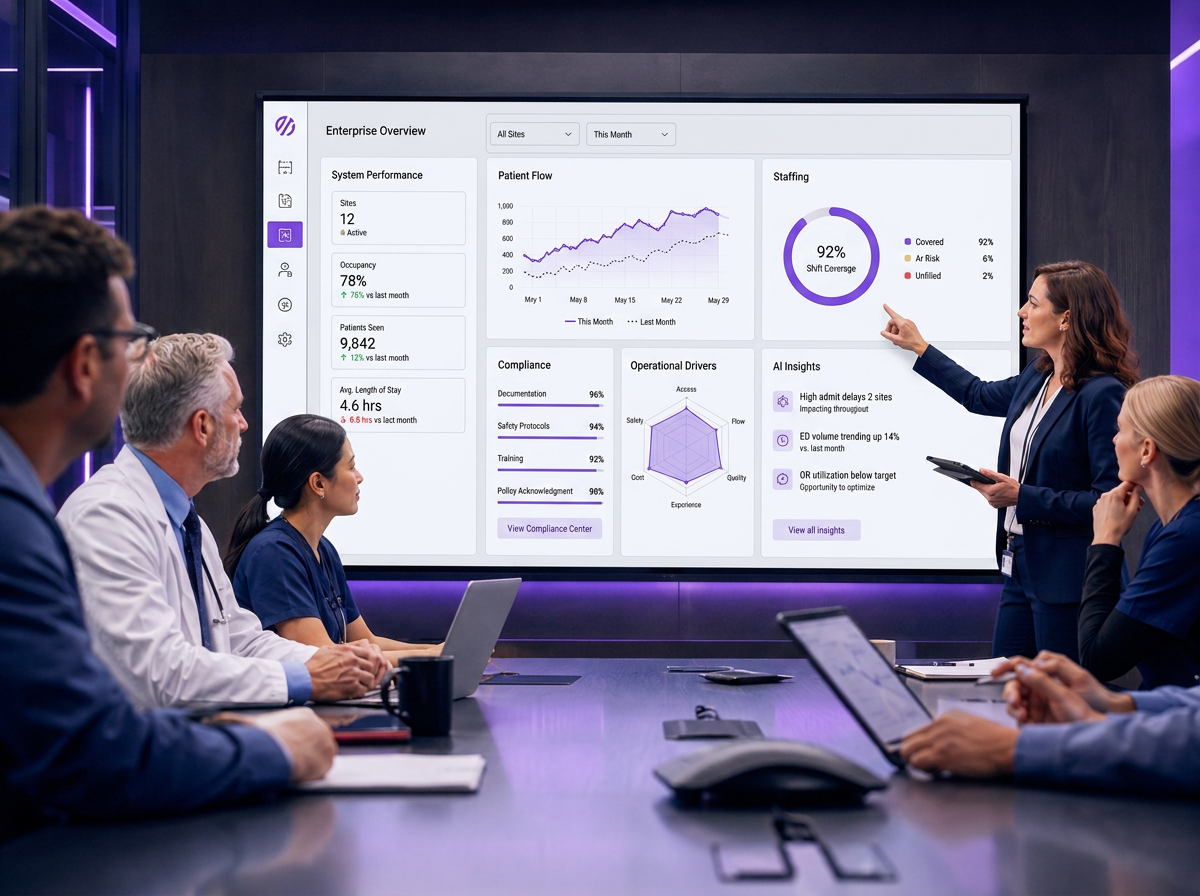
Rostering is one of the largest unpaid workloads in a multi-clinician practice, and it is almost entirely a constraint-solving problem: cover, scope, leave, room availability and demand. That makes it a strong fit for automation — not to replace the person who builds the roster, but to produce a draft that respects every constraint so the final version is a review, not a build.
The same logic applies to staffing forecasts. Predicting next term's session demand from booking history, no-show patterns and seasonal trends turns staffing from reactive to planned, which is where the real cost saving lives.
Automation that compounds
The first automation rarely changes much on its own. What changes the practice is the second and third: when reminders feed no-show data back into booking availability, when roster drafts pull from the same demand forecast, and when structured notes feed the reporting layer without re-keying. Each one is small; together they remove the admin layer that sits between clinicians and their patients.
- Automations should share one data model so they compound, not overlap
- Every automation needs an owner and a review cadence — drift is the silent failure
- Keep a human checkpoint on anything that reaches a patient or a record
Key takeaways
- Start AI on resented, high-volume, low-judgement admin — not on diagnosis
- Rostering and staffing forecasts are constraint problems automation handles well
- Value compounds when automations share one data model behind the scenes